
Cervical Transforaminal Epidural Steroid Injection
Sharp, burning, or electric-like pain traveling from the neck into the shoulder, arm, hand, or fingers may occur when a cervical spinal nerve root becomes irritated or inflamed. When a specific nerve root can be identified as the source of symptoms, a cervical transforaminal epidural steroid injection (CTFESI) may be considered as a targeted interventional treatment.
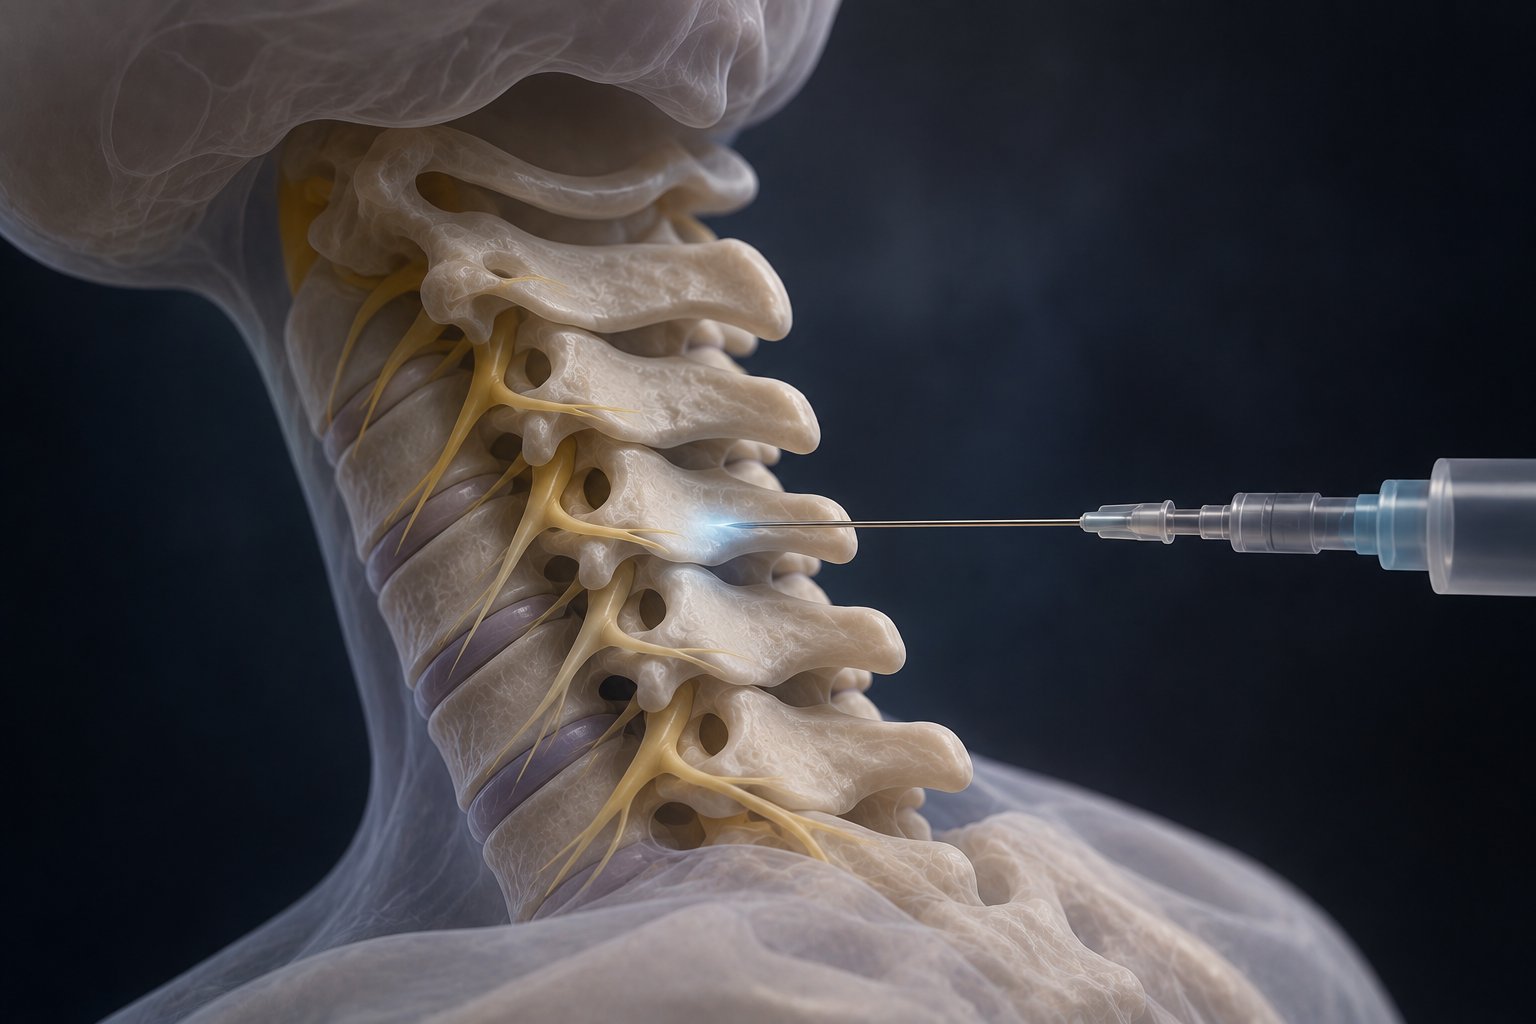
Targeted Treatment for Cervical Radiculopathy and Radiating Arm Pain
Unlike a broader epidural approach, a cervical transforaminal epidural injection is designed to deliver medication near a specific cervical nerve root as it exits the spine.
At TOPS Institute, we provide personalized evaluation for patients with cervical radiculopathy and other forms of nerve-related neck and arm pain in Los Angeles and Beverly Hills. When a cervical transforaminal epidural injection is clinically appropriate, careful patient selection, imaging review, image guidance, and procedural planning are essential.
A cervical transforaminal epidural steroid injection is a targeted procedure that delivers anti-inflammatory medication into the epidural region near a specific cervical spinal nerve root.
Spinal nerves exit the cervical spine through small openings called neural foramina.
When one of these nerves becomes irritated or inflamed, patients may develop cervical radiculopathy, commonly referred to as a pinched nerve in the neck.
The term transforaminal describes the approach toward the region of the neural foramen.
This allows medication to be delivered close to the affected nerve root.
The procedure does not remove a herniated disc, reverse degenerative changes, or permanently widen a narrowed neural foramen. Its purpose is to address inflammation contributing to nerve-related symptoms.
A cervical transforaminal epidural steroid injection may be considered for selected patients with cervical radicular painassociated with a specific nerve root.
Potential conditions may include:
- Cervical radiculopathy
- Pinched nerve in the neck
- Cervical disc herniation
- Cervical foraminal stenosis
- Selected cases of cervical spinal stenosis
- Degenerative cervical changes affecting a nerve root
Patients may experience symptoms such as:
- Radiating arm pain
- Shoulder pain
- Burning or electric-like pain
- Numbness
- Tingling
- Pins-and-needles sensations
- Changes in sensation
Because this procedure targets a particular nerve root, accurately identifying the source of symptoms is especially important.
Cervical radiculopathy develops when a nerve root in the neck becomes irritated or compressed.
Symptoms can extend along the pathway of the affected nerve into the:
- Shoulder
- Upper arm
- Forearm
- Hand
- Fingers
The precise distribution depends on which cervical nerve root is involved.
When inflammation surrounding an identifiable nerve root contributes to persistent radicular pain, a targeted transforaminal epidural injection may be considered.
A cervical disc herniation occurs when material from a spinal disc extends beyond its normal boundary.
If the displaced material irritates a nearby cervical nerve root, the patient may experience radiating arm pain, numbness, tingling, or other neurological symptoms.
A cervical transforaminal epidural steroid injection does not physically remove or repair the herniated disc.
Instead, medication is delivered near the affected nerve root to address inflammation associated with the disc herniation.
The neural foramina are openings along the sides of the cervical spine through which spinal nerves exit.
Cervical foraminal stenosis occurs when one or more of these openings become narrowed.
Potential causes include:
- Loss of disc height
- Bone spur formation
- Cervical spondylosis
- Facet joint degeneration
- Disc bulging or herniation
- Other degenerative changes
If narrowing irritates a cervical nerve root, patients may develop radicular symptoms.
A transforaminal injection may be considered in selected patients to deliver medication near the affected nerve.
The procedure does not physically widen the foramen.
It depends on the type of stenosis and symptoms involved.
When cervical narrowing affects an individual nerve root and produces radicular arm pain, an epidural injection may be considered for selected patients.
However, central cervical spinal stenosis involving significant spinal cord compression is different from isolated nerve-root irritation.
An epidural steroid injection does not decompress the spinal cord.
Patients with signs of cervical myelopathy, progressive neurological impairment, significant weakness, balance difficulties, or loss of hand coordination require appropriate evaluation and may need surgical consultation.
The procedure is designed to deliver medication close to an irritated cervical spinal nerve root.
Corticosteroid medication is used for its anti-inflammatory effects.
By reducing inflammation around the affected nerve, treatment may help decrease symptoms such as:
- Radiating arm pain
- Burning discomfort
- Electric-like pain
- Tingling
- Other nerve-related symptoms
A local anesthetic may also be used depending on the procedure and clinical circumstances.
The response varies between patients, and complete or permanent relief cannot be guaranteed.
Cervical transforaminal epidural injections require careful procedural planning because of the complex anatomy surrounding the cervical spinal nerves.
The procedure generally involves:
- 1The patient is positioned to provide access to the cervical spine.
- 2The treatment area is cleaned and prepared.
- 3Local anesthetic may be used to numb the skin and surrounding tissues.
- 4Using image guidance, the physician carefully directs the needle toward the appropriate foraminal region.
- 5Needle position is carefully evaluated before medication is administered.
- 6Contrast material may be used to assess positioning and distribution when clinically appropriate.
- 7Medication is delivered near the targeted cervical nerve root.
- 8The needle is removed, and the patient is monitored after the procedure.
The exact technique and medication selection are determined according to the patient’s anatomy, diagnosis, imaging findings, and individual risk factors.
The cervical spine contains the spinal cord, spinal nerves, and important blood vessels within a relatively compact anatomical area.
Precise image guidance allows the physician to visualize relevant bony anatomy and carefully position the needle.
Contrast imaging may also be used to evaluate medication flow and help identify unintended vascular placement before medication is administered.
Because a cervical transforaminal injection targets the region near a specific nerve root, meticulous technique is particularly important.
Both procedures deliver medication into the cervical epidural region, but they use different approaches.
Cervical Transforaminal Epidural Injection
The transforaminal approach targets the region near a specific cervical nerve root through the neural foramen.
Cervical Interlaminar Epidural Injection
The interlaminar approach accesses the epidural space through the posterior cervical spine, allowing medication to distribute within the epidural space.
The transforaminal approach offers more targeted delivery, but the appropriate technique must be selected after considering the patient’s:
- Diagnosis
- Anatomy
- Imaging
- Affected nerve
- Medical history
- Potential benefits
- Procedural risks
One approach should not automatically be considered better for every patient.
A cervical TFESI may be considered for carefully selected patients whose symptoms correspond to a particular cervical nerve root.
Potential candidates may include patients who:
- Have cervical radiculopathy
- Have persistent radiating arm pain
- Have a cervical disc herniation affecting a nerve root
- Have cervical foraminal stenosis
- Have nerve-related symptoms despite appropriate conservative treatment
- Have symptoms that correspond with examination and imaging findings
A cervical transforaminal injection is not generally intended to treat nonspecific neck pain without evidence of nerve-root involvement.
Not every patient with neck or arm pain is an appropriate candidate.
For example, pain primarily originating from the cervical facet joints may require a different diagnostic and treatment approach.
Patients with myofascial neck pain may benefit from treatment directed toward muscles and trigger points rather than the epidural space.
Patients with significant spinal cord compression or symptoms of cervical myelopathy may require specialist or surgical evaluation.
The correct diagnosis should determine the treatment.
The duration of pain relief varies considerably between patients.
Some patients may experience meaningful improvement for weeks or months, while others experience shorter or limited benefit.
Results depend on factors such as:
- Cause of nerve irritation
- Severity of symptoms
- Degree of structural compression
- Duration of symptoms
- Previous treatment
- Individual response
The procedure is generally one component of a broader treatment strategy.
The response is individualized.
Some patients may notice improvement relatively soon after treatment, while the corticosteroid’s anti-inflammatory effect may take several days to develop.
Temporary soreness or a temporary change in symptoms may occur after the injection.
Patients should follow their physician’s post-procedure instructions and report concerning or unexpected symptoms.
Cervical transforaminal epidural injections require particularly careful consideration because the treatment area contains important spinal and vascular structures.
Although complications are uncommon, rare but serious neurological and vascular complications have been reported with cervical transforaminal epidural injections.
Other potential risks and side effects may include:
- Temporary injection-site discomfort
- Temporary increase in pain
- Headache
- Bleeding
- Infection
- Medication-related effects
- Allergic reaction
- Nerve injury
- Blood vessel injury
- Other rare complications
Certain medications and medical conditions may affect procedural planning.
For this reason, patient selection, review of imaging, image guidance, medication selection, and careful procedural technique are important components of treatment.
The potential benefits, risks, and alternatives should be reviewed with each patient before proceeding.
Cervical transforaminal epidural steroid injections are generally outpatient procedures.
Patients are monitored following the injection and receive individualized instructions regarding activity and recovery.
Temporary soreness may occur around the treatment area.
When nerve-related pain improves, patients may be better able to participate in physical therapy, exercise, and other rehabilitation strategies.
The defining feature of a cervical transforaminal epidural injection is its ability to deliver medication near a specific cervical nerve root.
That precision also makes accurate diagnosis, imaging review, and careful procedural planning particularly important.
At TOPS Institute, we evaluate:
- The patient’s pain pattern
- Neurological symptoms
- Physical examination findings
- Cervical imaging
- The suspected nerve root
- Previous treatments
- Individual risk factors
before determining whether a cervical transforaminal epidural steroid injection is appropriate.
For carefully selected patients with cervical radiculopathy, cervical disc herniation, or cervical foraminal stenosis, targeted epidural treatment may help reduce nerve inflammation and improve function.
For patients seeking evaluation for cervical transforaminal epidural steroid injections in Los Angeles or Beverly Hills, TOPS Institute provides personalized interventional pain management focused on accurate diagnosis and appropriate treatment selection.
Frequently Asked Questions About Cervical Transforaminal Epidural Steroid Injections
A cervical transforaminal epidural steroid injection is a targeted procedure that delivers anti-inflammatory medication near a specific cervical spinal nerve root through the foraminal region.
Transforaminal refers to the approach toward the neural foramen, the opening through which a spinal nerve exits the cervical spine. This allows treatment to be directed near a particular nerve root.
It may be considered for selected patients with cervical radiculopathy caused by conditions such as cervical disc herniation or foraminal stenosis.
It may help selected patients when an identifiable cervical nerve root is inflamed and contributing to radiating arm pain. The procedure addresses nerve inflammation rather than physically removing the structure causing compression.
No. The injection does not repair or remove a herniated disc. It is intended to reduce inflammation around an affected nerve root and help manage radicular symptoms.
A cervical epidural steroid injection is the broader category. An interlaminar cervical epidural accesses the epidural space through a posterior approach, while a cervical transforaminal injection targets the region near a specific nerve root through the neural foramen.
Results vary. Some patients may experience improvement lasting weeks or months, while others may have shorter or limited relief.
They can be performed in carefully selected patients, but the cervical transforaminal approach has important potential risks, including rare serious neurological and vascular complications. Patient selection, imaging guidance, medication selection, and careful procedural technique are therefore particularly important.
No. It is a minimally invasive injection procedure and does not require a surgical incision or removal of spinal tissue.
Radiating pain from the neck into the arm or hand can result from several cervical spine conditions. Identifying the affected nerve and understanding why it is irritated are important before selecting an epidural approach.
Schedule a consultation with TOPS Institute in Los Angeles or Beverly Hills to determine whether a cervical transforaminal epidural steroid injection or another treatment may be appropriate for your cervical radiculopathy and arm pain.
Schedule an Appointment