
Most pain procedures aim to calm inflammation. Radiofrequency Ablation does something different: it interrupts the pain signal itself.
For patients whose relief from injections keeps fading after a few weeks, that difference can matter a great deal.
How it works
Sensory nerves carry pain signals from a joint to the brain. In radiofrequency ablation, a specialised needle is positioned next to the targeted nerve using fluoroscopic X-ray or ultrasound guidance. A small electrode delivers controlled radiofrequency energy, creating a precise thermal lesion that interrupts that nerve’s ability to transmit pain.
Importantly, RFA does not remove the painful joint or reverse arthritis. It reduces the transmission of pain from the affected area — which is often enough to restore movement, sleep and the ability to exercise.
The diagnostic step is the whole game
This is the part patients most often skip past, and it is the part that determines whether RFA works.
Before ablation, one or more diagnostic blocks are performed. For neck and back pain these are Medial Branch Blocks; for the knee, a genicular nerve block. A small amount of local anaesthetic is placed next to the nerves in question.
If numbing those specific nerves produces significant temporary relief, it strongly suggests they are carrying your pain — and that treating them is likely to help. If it does not, ablation is unlikely to work, and a different source should be investigated.
This is why we ask patients to pay close attention in the hours after a block, and to note what they can suddenly do that they could not before.
What it treats
Neck and back
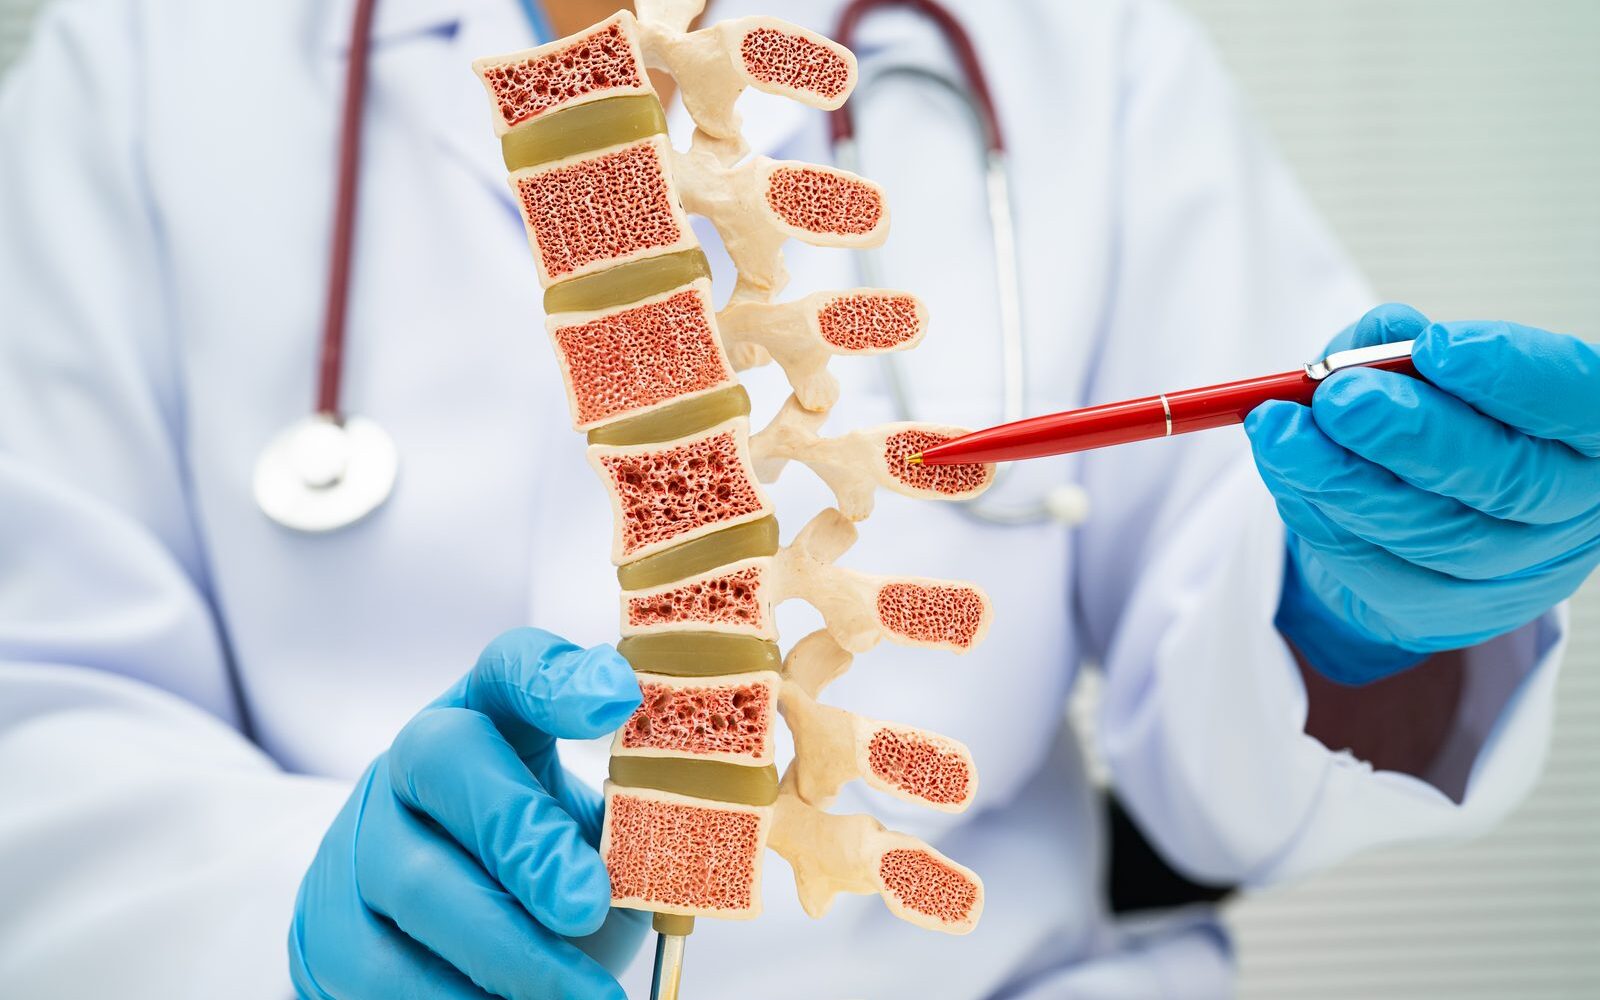
Cervical Radiofrequency Ablation and Lumbar Radiofrequency Ablation target the medial branch nerves supplying the facet joints — small joints along the back of the spine that commonly become arthritic.
Facet pain typically aches across the neck or lower back, worsens with extension, twisting or standing, and eases when bending forward. Unlike sciatica, it usually does not radiate below the knee in a defined nerve pattern.
Knee
Genicular Radiofrequency Ablation targets sensory nerves around the knee. It may be considered for knee osteoarthritis, chronic knee pain, persistent pain after knee replacement, or when surgery is less appropriate for medical reasons.
It does not repair cartilage. Its purpose is to reduce pain and improve function — and many patients use that window to participate more effectively in physical therapy and strengthening.
Sacroiliac joint
Sacroiliac Joint Radiofrequency Ablation targets the lateral branch nerves carrying pain from the back of the SI joint, for confirmed sacroiliac pain.
What the day looks like
The procedure is performed as an outpatient, generally with local anaesthetic and sometimes light sedation. After sterile preparation and image guidance, low-level electrical stimulation may be used to confirm the needle is near the intended sensory nerve and away from motor nerves. Energy is then applied.
Most procedures take roughly 30 to 60 minutes, though the full visit is longer with preparation and recovery.
Timeline for relief
Relief is not always immediate. Some patients notice improvement within several days; others take two to four weeks to feel the full benefit. Temporary soreness or a mild flare afterwards is common while the treated area settles.
Relief commonly lasts approximately six to twelve months, though this varies with the condition treated, the accuracy of the diagnosis, the severity of degeneration, and participation in rehabilitation.
When pain returns
Treated nerves can regenerate over time, which is why symptoms may eventually come back. This is expected rather than a failure. When the first procedure produced meaningful relief, repeat treatment is often appropriate.