
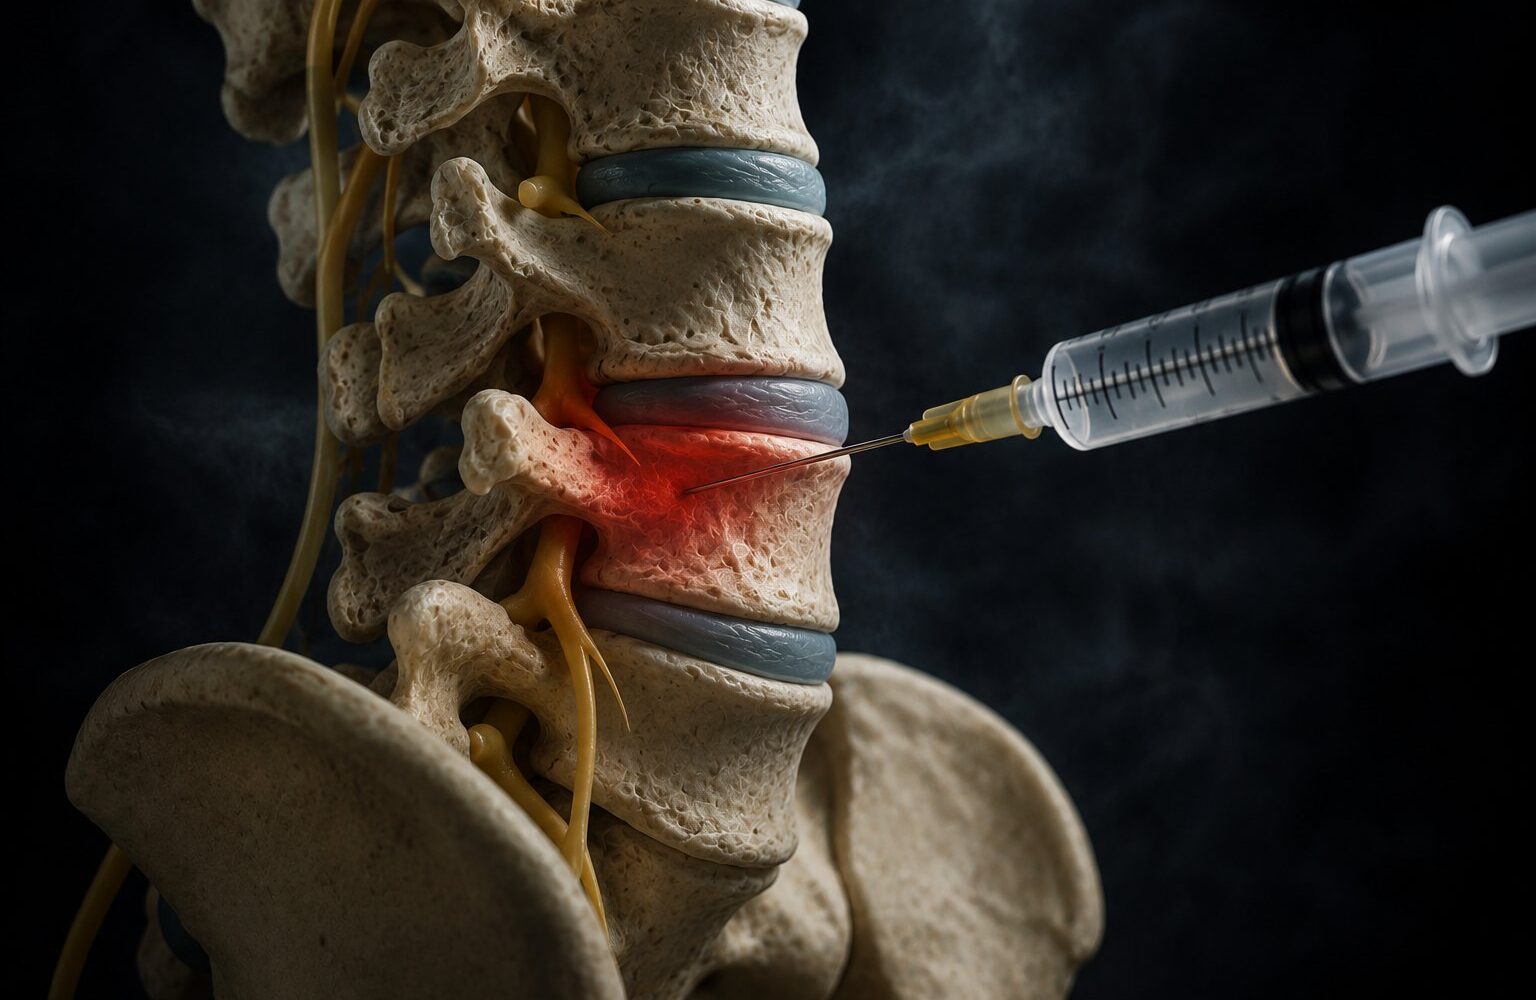
An epidural steroid injection is one of the most common procedures in interventional pain management — and one of the most misunderstood. Patients often arrive picturing the epidural used in childbirth, which is a different procedure with a different goal.
Here is what actually happens, and what it is for.
What the procedure does
The epidural space surrounds the spinal nerves. When a nerve root becomes irritated or inflamed — by a disc herniation, stenosis or degenerative change — pain often radiates away from the spine into an arm or a leg.
An Epidural Injection delivers anti-inflammatory medication into that space, close to the affected nerve. The goal is to reduce inflammation around the nerve, relieve radiating pain, and make movement and rehabilitation possible.
It is used for radiating, nerve-related pain rather than for localised mechanical back or neck pain. Pain arising from the facet joints is usually better addressed with Facet Joint Injections or Medial Branch Blocks.
Three approaches, chosen deliberately
The route to the epidural space is selected based on where the problem is and how selective the treatment needs to be.
Interlaminar
Medication is placed into the epidural space from the midline, spreading over several levels. A Lumbar Epidural Steroid Injection or Cervical Epidural Steroid Injection commonly uses this approach.
Transforaminal
The needle is directed toward a single nerve root where it exits the spine. A Lumbar Transforaminal Epidural Steroid Injection is more selective, which makes it useful both for treatment and for confirming which level is responsible.
Caudal
A Caudal Epidural Steroid Injection enters through the sacral hiatus at the base of the spine. It is often chosen for lower lumbar and sacral symptoms, or where previous surgery makes other approaches less suitable.
What happens on the day
- Review. Your physician confirms your symptoms, imaging, medications and any blood-thinning therapy.
- Positioning. You are positioned to open the target area, usually face down or seated.
- Sterile preparation. The skin is cleaned and numbed with local anaesthetic.
- Image guidance. Fluoroscopic X-ray guides the needle; contrast dye may confirm correct placement before medication is given.
- Injection. The medication is delivered. This part typically takes only a few minutes.
- Recovery. You are monitored briefly and usually go home the same day.
Most patients describe pressure rather than sharp pain. If sedation is used, you will need someone to drive you home.
How quickly it works
Two medications are often used, and they work on different timelines.
The local anaesthetic can relieve pain within hours — useful diagnostically, because it suggests the right structure was targeted. That effect wears off.
The steroid reduces inflammation more gradually, often over several days and sometimes up to two weeks.
A temporary increase in soreness in the first day or two is common and does not mean the injection failed.
How long relief lasts
This varies considerably. Some patients get weeks of relief, others several months, and some need a series of injections. Duration depends on the diagnosis, degree of nerve compression, how long symptoms have been present, and what happens afterwards.
That last point matters most. An injection creates a window in which movement is easier. Patients who use that window for physical therapy and strengthening tend to hold their improvement longer than those who simply wait for pain to return.
Risks worth knowing
Epidural injections are generally considered safe when performed by experienced physicians using image guidance. Potential risks include temporary increased pain, bleeding, infection, allergic reaction, steroid-related effects such as a short-term rise in blood sugar, temporary numbness or weakness, and rarely, nerve or vascular complications.
Patients taking blood thinners, or with active infection, bleeding disorders or uncontrolled diabetes, may need additional evaluation. Do not stop prescribed blood-thinning medication unless your physicians have given you coordinated instructions.